Contents include:
- Rambles
- What is economics
- School wasn’t a waste, I’m actually using what I’ve learned
- Some projects I’ve done [Eye health care report], [League tables]
I am often curious as to what exactly people do day to day. Some stuff is fairly straightforward. I am pretty sure I know what a bus driver or a teacher does, and I suspect you do too.
But there’s a lot of jobs I don’t know. White collar work is kinda indistinct from the outside – what does my friend in “Global Health logistics” do? How about a suffering acquaintance in “grant administration”? And then the mysterious “what exactly is a strategy consultant” question that I’ll have to interview my brother for (bro, comment if you are willing to do a podcast with me for the blog)
Economist is also a bit mysterious. At the highest level, “thinking about the economy” is so general as to be uninformative, and the exact tasks (reading research, building models, doing statistics, writing code, writing research) is indistinguishable from those in most other other quant jobs.
Economics is the study of making choices under scarcity. I’d estimate two-fifths of my work is about transportation infrastructure (airports, train stations, and transit planning guidance) and another two-fifths of my work is health, with a smattering of other sectors.
My health work has rolled into the station before any transport projects, so trains will need to wait for part two. I never anticipated working in health economics, but I shouldn’t exactly be surprised. In school, health examples showed up all over the place in math and statistics. I took a random public health course in undergrad (peak timing given covid), and then three of the profs teaching my MSc were mathematical biologists. One was a disease modeller for the province of Alberta and works at the Institute of Health economics.
Working in CEPA’s house practice, I’ve managed to touch at least half of what I’ve done in school. Even the queuing theory course, taken because queues are everyone’s favourite topic (see this approachable and fun video about queuing at Disney world), came in useful as I looked at NHS queues. That one was one of the most painful courses of my degree outside of intro to real analysis (math peeps know what I mean), but I did manage to take it with my brother. Dude smoked me of course, with an A+ to my A- in that bad boy. You all know Evan, I have never met anyone with a faster clock speed.
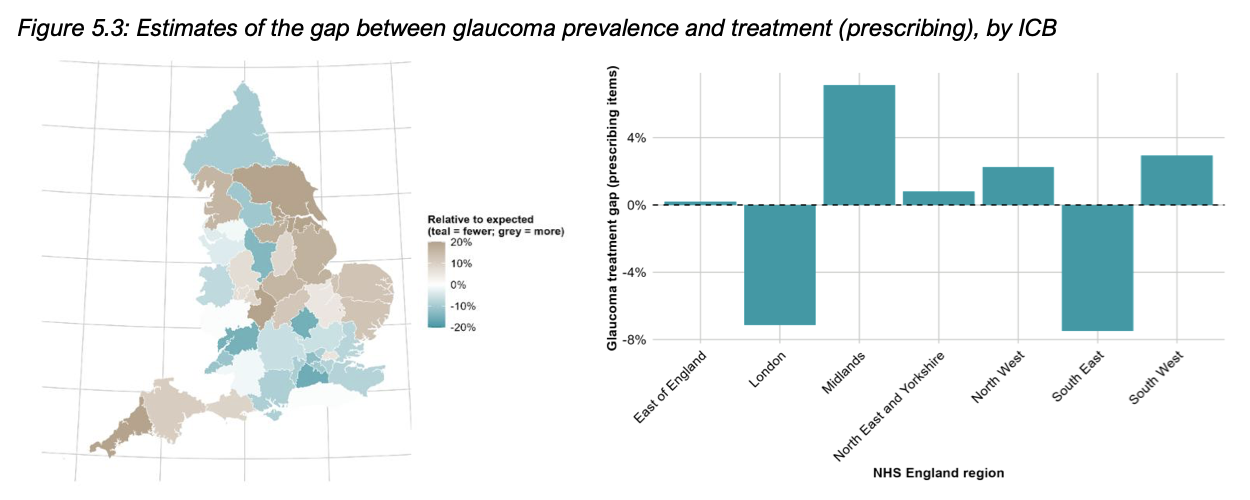
I’ve had three large health economics projects so far. The first one (to be published) was for Newmedica, a eye healthcare provider that has surgery centres for cataracts, glaucoma, AMD, and also owns the glasses company SpecSavers. They commissioned CEPA (aka my colleague David Jones and myself) to look into eye health-care disparities in the England, and to pull out the top 10 “Blindspots”, the regions with the worst eye care. In England, healthcare management is divided into 42 Integrated care boards (ICBs) [at the time of this article. It has now been reduced to 36].
Each care board gets funding from taxes to provide free healthcare to it’s residents (similar to Alberta). The care boards decide how to allocate it’s funding most efficiently to meet the health needs of it’s own population. They have some margin to experiment, such as running specialty cataract surgery centres, or paying private company to provide care.
Which brings us to the report. I won’t rehash exactly what I did to find the blind spots…
Because I very carefully wrote it up here [link]! Give it a skim, it’s full of pretty maps I made. No need to redo the work they pay me the big medium-bucks for. Our report was then used by Newmedica for a broader healthcare report, and ended up in the press, including the Telegraph.
Secondly, I analyzed the NHS league tables, which rank all healthcare trusts (aka hospitals or groups of hospitals) across England. This ranking system kinda works for finding out which trusts the government should be most concerned with, but has a lot of problems if you want to use it as a patient. You can read more about those here. I also built a dashboard to show different versions of these league tables I created to answer different questions about when a hospital might be better than another.
My final large health project, still ongoing, is analyzing a large health NGO’s work in rebuilding third world healthcare systems after covid. I’ve signed a NDA, so if the paper is published formally I’ll give my NDS read through and figure out I’d be allowed to reprint.
So what do I do day to day? Well for a generalist economist in my position: background research from academia and government sources, compile datasets, do statistics/economics/econometric modelling, and write a report. It’s exactly like school, except it pays more now.
Health isn’t quite the field I wanted to end up in, but I’ve enjoyed it nonetheless. Stay tuned for my next publication which was right in my field: Local Economic Development impacts of train station (re)development!

Leave a Reply